Acrochordon Skin Tags: Causes, Removal Options and What to Expect
Acrochordons, more commonly known as skin tags, are among the most frequently encountered benign skin growths in adults. Although they are harmless in the vast majority of cases, they can cause discomfort when they catch on clothing or jewellery, and many people choose to have them removed for cosmetic or practical reasons. This article explains what acrochordons are, why they develop, which removal methods are available, what the treatment experience involves, and how to decide whether professional removal may be appropriate for you.
Key Takeaways
- Acrochordons are benign, soft skin growths attached by a narrow stalk; they are not cancerous and do not become cancerous.
- They are extremely common, particularly in adults over 40, and are associated with friction, hormonal changes, and metabolic factors such as insulin resistance.
- Several effective removal methods exist, including cryotherapy, electrocautery, surgical excision, and ligation; the most appropriate option depends on the size, location, and number of lesions.
- Self-removal at home carries real risks, including bleeding, infection, and scarring; professional assessment is advisable before any removal attempt.
- Any skin lesion that changes in colour, bleeds spontaneously, or looks atypical should be assessed by a qualified clinician before treatment.
What Is an Acrochordon?
An acrochordon is a small, soft, flesh-coloured or slightly pigmented growth that protrudes from the skin surface on a thin stalk called a peduncle. The term comes from the Greek words for extremity and cord, which describes the characteristic hanging appearance. Acrochordons are also referred to as skin tags, fibroepithelial polyps, soft fibromas, or cutaneous papillomas, though all of these terms describe the same benign lesion. Histologically, an acrochordon consists of a loose fibrovascular core covered by a thin layer of epidermis, which explains its soft, compressible texture.
Acrochordons range considerably in size. Most are between one and five millimetres in diameter, but larger variants, sometimes called giant acrochordons, can reach several centimetres. They are typically painless unless subjected to repeated friction, twisting, or pressure. When the blood supply to the stalk is interrupted, the lesion may darken and become tender before eventually falling off, a process that can occur spontaneously but is not a reliable or safe method of self-management.
How Common Are Skin Tags and Who Gets Them?
Acrochordons are one of the most prevalent benign skin lesions in the general population. Estimates suggest that nearly half of all adults will develop at least one acrochordon during their lifetime, with prevalence increasing significantly after the age of 40. They affect men and women in roughly equal proportions, though certain risk factors may increase the likelihood of developing multiple lesions.
Established associations include obesity and being overweight, type 2 diabetes and insulin resistance, pregnancy, and a family history of skin tags. The link with insulin resistance is particularly well documented; elevated insulin levels are thought to stimulate keratinocyte and fibroblast proliferation, contributing to the formation of these growths. Acrochordons are also more common in people with metabolic syndrome, and their presence in large numbers has occasionally prompted clinicians to consider screening for underlying glucose dysregulation, though skin tags alone are not a diagnostic criterion for any metabolic condition.
Friction appears to play a central mechanical role. Acrochordons most commonly develop in skin folds and areas where skin rubs against skin or clothing, including the neck, axillae (armpits), groin, inframammary folds beneath the breasts, and the eyelids. The repeated mechanical irritation in these locations is thought to trigger localised epidermal proliferation over time.
Are Acrochordons Dangerous?
Acrochordons are benign lesions with no malignant potential. They do not transform into skin cancer and are not associated with any internal disease on their own. However, it is important not to assume that every small skin growth is a harmless acrochordon. Several other skin lesions can superficially resemble skin tags, including seborrhoeic keratoses, dermal naevi (moles), neurofibromas, warts caused by human papillomavirus, and, in rare cases, pedunculated basal cell carcinomas or other malignant lesions.
A qualified clinician should assess any lesion that is rapidly growing, has an irregular border, contains multiple colours, bleeds without trauma, or appears in an unusual location. Dermoscopy, a non-invasive technique using a magnifying instrument with polarised light, can help distinguish acrochordons from other lesions and is routinely used in dermatological practice. If there is any clinical uncertainty, the removed tissue may be sent for histological examination to confirm the diagnosis.
Removal Methods for Acrochordons
Several well-established techniques are used to remove acrochordons in a clinical setting. The choice of method depends on the size, location, and number of lesions, as well as patient preference, skin type, and the practitioner’s available equipment. No single method is universally superior; each has specific advantages and limitations.
Cryotherapy
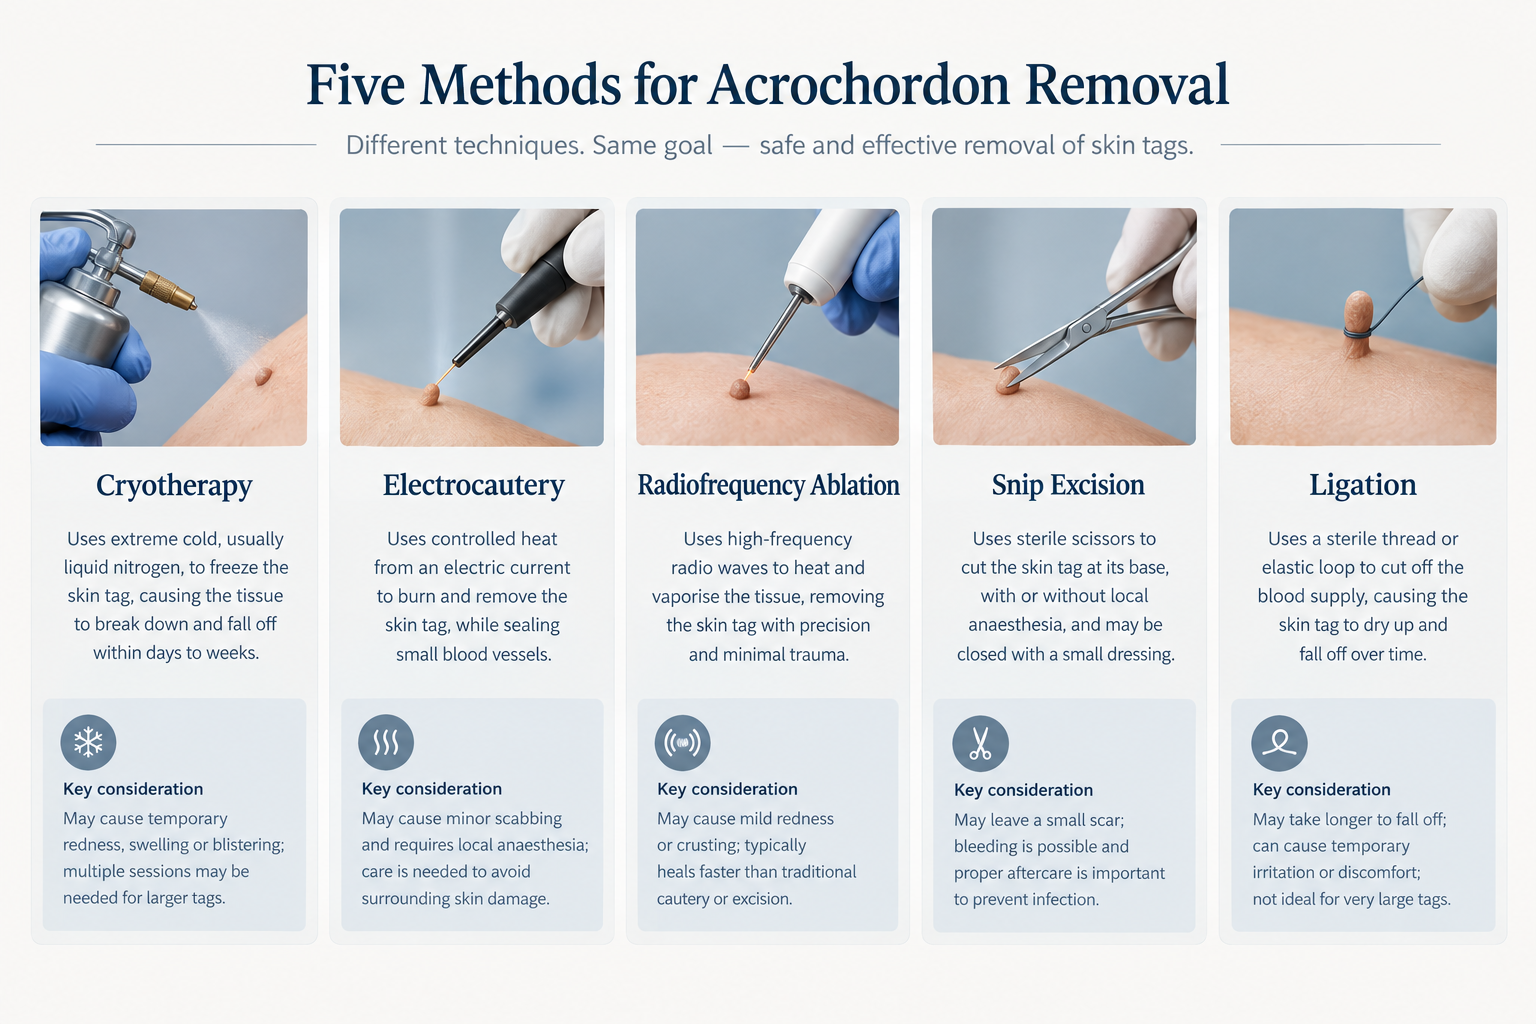
Cryotherapy involves applying liquid nitrogen or a similar cryogen directly to the acrochordon, causing rapid freezing and destruction of the tissue. The treated lesion typically blisters, darkens, and falls off within one to two weeks. Cryotherapy is well suited to small and medium-sized acrochordons and can treat multiple lesions in a single session. Potential side effects include temporary redness, blistering, post-inflammatory hypopigmentation (lightening of the skin), and, less commonly, hyperpigmentation. Pigmentation changes are more likely in individuals with darker skin tones, and this should be discussed during the pre-treatment consultation. Cryotherapy is generally quick and does not require local anaesthesia for small lesions, though larger growths may benefit from it.
Electrocautery and Radiofrequency Ablation
Electrocautery uses an electrical current to generate heat that destroys the acrochordon tissue. Radiofrequency ablation works on a similar principle but uses high-frequency radio waves, which can offer more precise tissue destruction with potentially less surrounding thermal damage. Both techniques are effective for lesions of varying sizes and allow the practitioner to control the depth and extent of treatment. Local anaesthetic is typically applied beforehand. A small scab forms at the treatment site and resolves over one to two weeks. Risks include temporary redness, scabbing, and a small risk of scarring or pigmentation change, particularly if aftercare instructions are not followed.
Surgical Excision and Snip Excision
Snip excision involves cutting the acrochordon at its stalk using sterile scissors or a scalpel under local anaesthesia. This is one of the most straightforward and reliable methods, particularly for pedunculated lesions with a well-defined stalk. The procedure takes only a few minutes per lesion, and the removed tissue can be sent for histological analysis if there is any diagnostic uncertainty. Bleeding is usually minimal and controlled with pressure or a haemostatic agent. Scarring is generally minimal when the technique is performed carefully, though individual healing responses vary.
Ligation
Ligation involves tying a fine suture or thread tightly around the base of the acrochordon stalk, cutting off its blood supply. The lesion gradually darkens and falls off over several days to a couple of weeks. This technique is sometimes used for larger pedunculated lesions. When performed by a trained practitioner using sterile materials, ligation is effective and carries a low risk of complications. Home ligation kits are commercially available, but their use without professional guidance carries risks of incomplete removal, infection, and scarring.
Laser Treatment
Certain laser systems, including carbon dioxide lasers and erbium lasers, can be used to ablate acrochordons. Laser treatment offers precision and may be particularly useful for lesions in sensitive areas such as the eyelids. It typically requires local anaesthesia and may involve a slightly longer recovery period than simpler methods. Laser removal tends to be more expensive than other techniques and is not universally available in all clinical settings.
What Happens During a Professional Removal Appointment?
A professional acrochordon removal appointment typically begins with a clinical assessment of the lesion or lesions. The practitioner will examine the growth, confirm the diagnosis, and discuss the most appropriate removal method based on the size, location, and number of acrochordons. Any lesion that appears atypical will be assessed more carefully before treatment proceeds.
For most small acrochordons, the procedure itself takes only a few minutes. Local anaesthetic cream or an injectable local anaesthetic may be applied to minimise discomfort, depending on the method chosen and the sensitivity of the area. The removal is generally well tolerated. Afterwards, the treated site may appear red, slightly swollen, or have a small scab. The practitioner will provide aftercare instructions, which typically include keeping the area clean and dry, avoiding picking at any scab, and applying a recommended topical preparation if appropriate.
Most people can return to normal activities immediately or within a day. Healing is usually complete within one to three weeks, depending on the method used and the size of the lesion. Larger lesions or those in areas subject to friction may take slightly longer to heal fully.
Risks and Potential Side Effects
Professional acrochordon removal is generally considered low-risk when performed by a qualified practitioner in an appropriate clinical environment. However, as with any skin procedure, potential side effects and complications exist and should be understood before treatment.
- Temporary redness and swelling at the treatment site are expected and usually resolve within a few days.
- Scabbing and crusting are a normal part of the healing process and should not be picked or scratched.
- Pigmentation changes, including hypopigmentation or hyperpigmentation, are possible, particularly with cryotherapy or laser treatment, and are more likely in individuals with darker skin tones.
- Scarring is uncommon when appropriate technique is used, but a small scar or textural change is possible, especially with larger lesions or in individuals prone to keloid or hypertrophic scarring.
- Infection is a risk with any skin procedure; following aftercare instructions carefully reduces this risk significantly.
- Incomplete removal can occur, particularly with cryotherapy, and a second treatment session may occasionally be needed.
- Recurrence is possible; removing an acrochordon does not prevent new ones from forming, particularly if the underlying risk factors such as friction or metabolic factors remain present.
Individuals with a history of keloid scarring, bleeding disorders, or those taking anticoagulant medications should discuss these factors with their practitioner before any removal procedure. Removal of acrochordons on the eyelids requires particular care and should only be performed by a practitioner with appropriate experience in periocular procedures.
Why Professional Removal Is Preferable to Home Methods
A range of home removal products and methods are marketed for skin tags, including over-the-counter freezing kits, ligation devices, and topical preparations. While some of these products may be effective for very small, clearly identifiable acrochordons, home removal carries meaningful risks that are worth understanding before attempting it.
The most significant concern is diagnostic uncertainty. Without clinical training, it is not possible to reliably distinguish an acrochordon from other skin lesions, some of which may require medical attention. Attempting to remove a lesion that is not a simple skin tag could delay diagnosis of a more significant condition. Additionally, home procedures performed without sterile technique carry a risk of infection, and inadequate haemostasis can lead to prolonged bleeding. Scarring is also more likely when removal is performed without appropriate tools and technique. For these reasons, professional assessment before any removal attempt is advisable, particularly for lesions that are large, rapidly growing, pigmented, or located near the eyes.

Who May Be Suitable for Acrochordon Removal?
Most adults with confirmed acrochordons are suitable candidates for professional removal. Removal may be particularly worth considering when a skin tag is causing physical discomfort due to friction or catching on clothing, when it is in a cosmetically sensitive location, or when its appearance is causing distress. There is no medical requirement to remove acrochordons that are asymptomatic and clearly benign, but removal is a reasonable personal choice.
Suitability for specific removal methods may be influenced by skin type and tone, the size and location of the lesion, medical history including bleeding tendencies or immunosuppression, current medications, and whether the individual is pregnant. A thorough consultation allows the practitioner to identify the most appropriate approach and to flag any factors that might affect the procedure or healing.
Can Acrochordons Be Prevented?
There is no guaranteed way to prevent acrochordons from forming, but certain measures may reduce the likelihood of new lesions developing. Managing body weight can reduce skin-on-skin friction in fold areas and may also improve insulin sensitivity, addressing one of the proposed biological mechanisms. Wearing loose-fitting clothing that minimises friction in susceptible areas such as the neck and underarms may also be helpful. For individuals with diabetes or insulin resistance, optimising metabolic control is important for overall health and may have a secondary benefit in reducing the tendency to develop new skin tags, though this has not been definitively established in clinical trials.
It is worth noting that even after successful removal, new acrochordons can develop over time, particularly in individuals with multiple predisposing factors. Removal addresses existing lesions but does not alter the underlying tendency to form them.
Alternatives to Removal
For acrochordons that are small, asymptomatic, and clearly benign, watchful waiting is a perfectly reasonable approach. Many people choose to leave skin tags untreated indefinitely without any adverse consequences. If a lesion is causing friction-related irritation, protective padding or adjusting clothing choices may reduce discomfort without requiring removal.
Where removal is desired, the choice between cryotherapy, electrocautery, snip excision, ligation, and laser treatment represents a selection among alternatives rather than a comparison between treatment and no treatment. The practitioner’s recommendation will be guided by clinical factors, but patient preference regarding recovery time, cost, and tolerance for discomfort also plays a role in the decision.
Frequently Asked Questions
Do acrochordons grow back after removal?
The removed acrochordon itself does not regrow once the stalk has been fully destroyed or excised. However, new acrochordons can develop in the same general area or elsewhere on the body, particularly if the underlying risk factors such as friction, obesity, or insulin resistance remain present. Removal is not a permanent solution to the tendency to form skin tags.
Is acrochordon removal painful?
Most removal procedures involve minimal discomfort when local anaesthetic is used. Small lesions treated with cryotherapy may cause a brief stinging or burning sensation during the freeze. Snip excision and electrocautery are typically performed after topical or injectable anaesthetic, making the procedure itself largely painless. Some tenderness at the treated site is normal for a few days afterwards.
How long does healing take after skin tag removal?
Healing time varies depending on the removal method and the size of the lesion. Small acrochordons treated with cryotherapy or snip excision typically heal within one to two weeks. Larger lesions or those treated with laser may take up to three weeks to heal fully. Following aftercare instructions carefully supports optimal healing and reduces the risk of complications.
Will removing a skin tag leave a scar?
Scarring is uncommon after professional removal of small acrochordons, but a faint mark or slight textural change is possible, particularly with larger lesions. Individuals with a personal or family history of keloid or hypertrophic scarring have a higher risk of a more noticeable scar and should discuss this with their practitioner before treatment.
Can acrochordons be a sign of an underlying health condition?
Acrochordons are associated with insulin resistance, type 2 diabetes, obesity, and metabolic syndrome, but having skin tags does not confirm any of these diagnoses. If you have multiple acrochordons and have not had a recent health check, it may be worth discussing this with your GP, particularly if you have other risk factors for metabolic conditions. Skin tags alone are not a diagnostic criterion for any systemic disease.
Is it safe to remove a skin tag at home?
Home removal carries risks including infection, bleeding, scarring, and the possibility of treating a lesion that is not actually a benign acrochordon. Professional assessment is advisable before any removal attempt, particularly for lesions that are large, pigmented, rapidly growing, or located near the eyes. If home removal is being considered for a very small, clearly identifiable lesion, discussing the options with a clinician first is still the safer approach.
Does health insurance cover acrochordon removal?
In most cases, removal of acrochordons for cosmetic reasons is not covered by health insurance or publicly funded healthcare systems, as the lesions are benign and not medically necessary to remove. Coverage may vary depending on the specific policy and the clinical circumstances; it is worth checking with your insurer or healthcare provider if cost is a consideration.
Deciding Whether Acrochordon Removal Is Right for You
Acrochordons are benign, common, and in most cases require no treatment from a purely medical standpoint. The decision to have them removed is personal and may be driven by physical discomfort, cosmetic preference, or simply the desire to address something that has become a source of self-consciousness. All of these are valid reasons to seek a professional consultation.
The most important first step is to have any suspicious or unfamiliar skin lesion assessed by a qualified clinician before assuming it is a harmless skin tag. Once a diagnosis is confirmed, the range of available removal methods means that an appropriate option can usually be found for most lesions and most patients. Recovery is typically straightforward, and the risk of significant complications is low when treatment is carried out by an experienced practitioner in a suitable clinical environment.
If you are considering acrochordon removal, a consultation with a qualified dermatologist, aesthetic practitioner, or GP with experience in minor skin procedures is the appropriate starting point. They can confirm the diagnosis, recommend the most suitable removal method for your specific lesions, and ensure that any relevant medical factors are taken into account before treatment proceeds.